Eardrum repair is a surgical procedure to close a hole in the eardrum that has not healed on its own and to restore the protective barrier of the middle ear. Known medically as tympanoplasty, or myringoplasty when only the eardrum itself is repaired, the operation aims to stop recurrent ear discharge and to preserve or improve hearing. In adults, the hole is most often the result of long-standing chronic middle ear infection, and sometimes of a blow to the ear or a sudden pressure change.
What Is Eardrum Repair?
The eardrum (tympanic membrane) is a thin, semi-transparent layer about 1 centimeter across that separates the ear canal from the middle ear. It vibrates with sound and passes these vibrations to the three tiny hearing bones behind it: the malleus, incus and stapes. It is also a natural barrier that keeps water, bacteria and debris out of the middle ear.
When a hole (perforation) forms, both functions suffer. Sound is conducted less efficiently, the middle ear is left open, and infections become more likely, especially after contact with water. Eardrum repair closes the opening with a graft, a small patch of the patient’s own tissue. If needed, inflamed tissue can be cleared and damaged hearing bones repaired during the same operation.
Myringoplasty vs. Tympanoplasty
Myringoplasty means closing the eardrum only; it is sufficient when the middle ear and hearing bones are healthy. Tympanoplasty is broader: in addition to repairing the eardrum, it includes inspecting the middle ear, removing infected tissue and, when necessary, rebuilding the chain of hearing bones (ossiculoplasty). The approach is planned from the examination and tests, and confirmed during surgery according to how the middle ear looks.
Who Is a Candidate for Eardrum Repair?
Not every hole in the eardrum needs surgery. Small perforations caused by injury or pressure often close by themselves within a few weeks to three months, and keeping the ear dry with regular check-ups may be all that is required. Surgery is considered when the hole becomes permanent or causes ongoing problems.
Common Causes of Eardrum Perforation in Adults
- Chronic middle ear infection: Infections recurring over the years thin the eardrum and leave a permanent hole. This is the most common cause in adults.
- Trauma: Cleaning the ears with cotton swabs, hairpins or matches, a slap to the ear or a fall can tear the eardrum.
- Sudden pressure change (barotrauma): An airplane’s descent, ascending too quickly while diving or the pressure wave of an explosion can rupture it.
- Effects of earlier treatment: A hole that never closed after a childhood ventilation tube came out may keep causing problems in adulthood.
- Welding and hot objects: Sparks or hot metal entering the ear canal can, rarely, cause serious damage.
What Symptoms Does a Perforated Eardrum Cause?
A small hole may go unnoticed for years and be found only during a routine ear examination. With larger perforations, hearing loss becomes obvious; people start holding the phone to the other ear or missing conversations in noisy places. In chronic infection, recurrent and sometimes foul-smelling discharge after showering or swimming is typical. After a sudden injury, sharp pain, slight bleeding, ringing in the ear (tinnitus) and brief dizziness may occur.
Factors That Influence the Decision to Operate
A hole that has not closed for more than three months, recurrent discharge, hearing loss, the constant need to keep water out of the ear and work requirements all weigh in the decision. Repair may also be recommended for people who want to keep swimming or diving, or whose job requires a healthy eardrum. If a skin cyst called a cholesteatoma is suspected in the middle ear, surgery becomes even more important.
Preparation and Examination Before Surgery
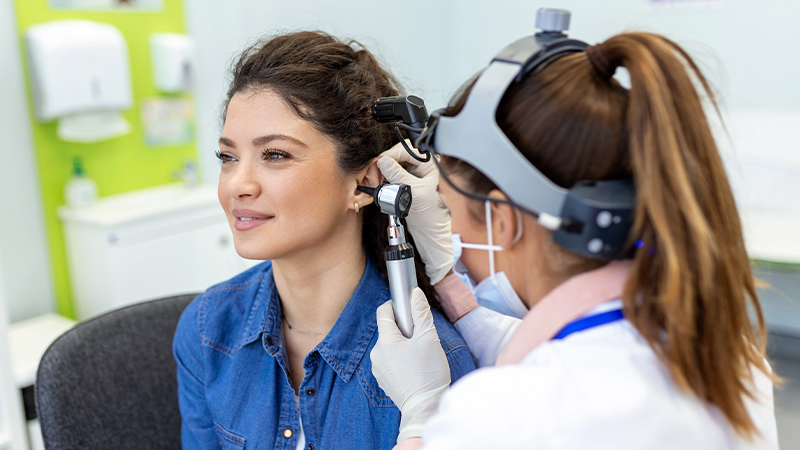
Evaluation begins with a detailed examination of the eardrum under a microscope or endoscope. The location, size and edges of the hole and the appearance of the middle ear lining are recorded. Whether the ear is actively draining also matters; ideally, the ear stays dry for a few weeks before surgery.
A hearing test (audiometry) shows the type and degree of hearing loss. If the conductive loss is greater than the size of the hole would explain, a problem with the hearing bones may be suspected. A CT scan of the temporal bone may be requested in chronic infection, suspected cholesteatoma or after previous ear surgery. Patients traveling from abroad are encouraged to bring earlier hearing tests, scan reports and a list of their medications.
What to Do Before Surgery
- Tell your doctor about all medications, especially blood thinners and herbal supplements.
- If you smoke, stopping at least a few weeks before surgery helps the graft receive a good blood supply and take hold.
- A draining ear should first be dried with the drops your doctor recommends.
- Follow the fasting instructions for general anesthesia; routine blood tests are done beforehand.
- Arrange for someone to accompany you on the day of surgery and plan a few days off work.
How Is Eardrum Repair Performed?
Eardrum repair is performed under general anesthesia and usually takes 1 to 3 hours, depending on the size of the hole and any additional work in the middle ear. It is carried out under magnification with an operating microscope or an endoscope.
Surgical Approaches
- Through the ear canal (transcanal approach): The eardrum is reached without an external incision. The endoscopic technique is the most common form and is preferred for suitable perforations.
- Behind the ear (postauricular approach): An incision in the natural crease behind the ear gives a wide view. It suits large perforations toward the front of the eardrum or a narrow ear canal.
- At the ear canal entrance (endaural approach): A small incision at the canal opening; an option for some medium-sized perforations.
Graft Selection and Techniques
The tissue most often used is temporalis fascia, the thin layer covering the temple muscle above and behind the ear. Cartilage from the tragus, the small flap in front of the ear opening, and its covering layer (perichondrium) are also common. Because cartilage is sturdier, it helps with recurrent perforations, poor Eustachian tube function and an eardrum that tends to collapse inward. For very small holes, a fat graft from the earlobe is another option.
The graft can be placed under the eardrum (underlay) or between its outer layers (overlay). The surgeon freshens the edges of the hole to stimulate healing, positions the graft and places dissolvable packing in the ear canal to hold it in place. Eroded hearing bones can be rebuilt with the patient’s own bone or a prosthesis. In some situations, such as extensive cholesteatoma, the repair may be planned in two stages.
Recovery After Eardrum Repair
Most patients go home on the day of surgery once the anesthesia has worn off. In the first days, fullness, mild pain, crackling or sloshing sounds are expected; they are caused by the packing in the ear canal. Pain is usually controlled with simple pain relievers.
Returning to Work and Daily Life
Most adults with desk jobs return to daily life and work within 1 to 2 days. For heavy lifting, bending or straining, as in construction or warehouse work, waiting two to three weeks is generally advised, because these movements raise middle ear pressure and can strain the graft. Gym workouts and strenuous exercise resume after a check-up.
Precautions in the First Weeks
- Keep the ear dry until your doctor says otherwise; a cotton ball coated with petroleum jelly can be placed at the ear opening while showering.
- Do not blow your nose forcefully, and sneeze with your mouth open.
- If the packing starts to come out, do not pull it; it will be cleaned at your check-up.
- Avoiding colds helps prevent infections spreading from the nose and throat to the middle ear.
Flying and Diving
Changes in cabin pressure can put the healing graft at risk, so flying is generally avoided for the first several weeks; many ENT teams suggest around four to six weeks, sometimes longer. If travel cannot be postponed, consult your doctor first and equalize pressure during descent by swallowing or chewing gum. Scuba diving places far greater stress on the ear and should be discussed no earlier than a few months after surgery, once an examination confirms full healing and good Eustachian tube function.
Notes for Patients Traveling from Abroad
International patients should plan to stay in Istanbul at least until the first check-up, usually one to two weeks after surgery, when part of the packing is removed and the ear is examined. Because flying is commonly postponed for several weeks after eardrum repair, discuss travel dates with your surgeon before booking; your surgeon will advise when air travel is reasonable in your case. Later check-ups, including the hearing test at around two to three months, can generally be coordinated with an ENT specialist at home, with results shared remotely.
Follow-Up and Hearing Results
Hearing improvement may not be noticeable right away, because the packing takes time to dissolve and middle ear swelling takes time to settle; a new hearing test is done about 6 to 12 weeks later. Follow-up visits check whether the graft has taken and how well the middle ear is ventilated. After surgery for chronic infection or cholesteatoma, longer follow-up is recommended to make sure the problem has not returned.
Possible Risks and Important Considerations
Eardrum repair is a commonly performed operation that gives good results in most patients. As with any surgery, however, there are risks that should be discussed openly beforehand.
- The graft may fail to take, or a new hole may form over time; a second repair can then be planned.
- Temporary taste change, because the taste nerve running behind the eardrum can be affected; this usually improves within weeks.
- Ear infection and discharge, tinnitus or temporary dizziness.
- Hearing may not improve as expected or, rarely, may decrease.
- Very rarely, injury to the facial nerve.
Contact your doctor without delay if you notice fever, worsening pain, foul-smelling or bloody discharge, significant dizziness, weakness on one side of the face or a sudden drop in hearing.
Eardrum Repair: Frequently Asked Questions
Can a hole in the eardrum close on its own?
Many small perforations caused by injury or pressure close within a few weeks. Holes linked to chronic infection, with thickened edges and present for more than three months, usually do not heal on their own and need surgical repair.
Will there be stitches?
Endoscopic surgery through the ear canal involves no external incision or stitches. When the operation is done from behind the ear, the incision lies in the crease behind the ear and is usually not visible once healed.
When can I swim after tympanoplasty?
An examination must first confirm that the eardrum has fully healed. For most patients this takes from a few weeks to two months; a longer wait is advised before diving.
How successful is eardrum repair?
Success rates for closing the eardrum are generally reported as high in the medical literature. The outcome depends on the size of the hole, infection in the middle ear, Eustachian tube function and personal factors such as smoking.
If both ears have holes, can they be operated on together?
Usually the ear with poorer hearing or more frequent discharge is treated first. The other ear is planned once the first has healed and its hearing result is assessed, so that hearing is preserved in at least one ear during recovery.
Conclusion
Adults with a hole in the eardrum, recurrent ear discharge or reduced hearing are evaluated in detail by ENT specialist Op. Dr. Tayfun Demirel at the practice in Ataşehir, Istanbul. Based on the examination and hearing test results, the likelihood of the hole closing on its own, the appropriate surgical approach and the choice of graft are planned individually. To book an appointment or ask for more information, please contact the clinic. This article is for informational purposes only; an in-person examination is required for diagnosis and treatment.
